Fraser-Kirk Plastic Surgery
Sunshine Coast
Level 3/37 The Esplanade,
Maroochydore QLD 4558
Patient profile
Age: 51 | Sex: Male | Previous surgery: None | Photography: Preoperative & 6 weeks postoperative
This case describes a 51-year-old male patient with a longstanding constitutional pattern of submental and submandibular fullness and an obtuse cervicomental angle — the same combination of features present in his father and other first-degree male relatives, and present since early adulthood rather than acquired with age. Layered over that pattern were changes consistent with his age, including prominent nasolabial folds and moderate jowling overlying the mandibular border. Bilateral upper eyelid dermatochalasis had also developed over recent years, encroaching on his superior visual field and most noticeable in low light and while driving at night.
The operative objectives were correction of the submental and submandibular fullness at its anatomical source, repositioning of the descended facial soft tissues, placement of structural volume along the mandibular border and midface, and excision of the redundant upper eyelid skin encroaching on the visual field.
Clinical evaluation identified the following features, reflecting both a longstanding constitutional pattern of neck and jawline morphology and changes consistent with his age:
The operative plan combined a deep plane face and neck lift, a formal deep neck reduction, and structural autologous fat grafting to the mandibular border and face. Each component acts on a different anatomical layer. The lift addresses soft tissue descent and skin excess, repositioning the face and neck as a connected unit. Deep neck reduction addresses the structures beneath the platysma — the submandibular glands, the anterior bellies of digastric, and the subplatysmal fat — which a lift does not reach. Fat grafting places volume in the regions identified as volume-deficient at assessment.
The distinction between constitutional morphology and age-related change governed the plan. Because the submental and submandibular fullness had been present since early adulthood and lay deep to the platysma, a face and neck lift addressing skin and platysma alone would act on the surface layers while leaving the ptotic submandibular gland, the hypertrophic digastric and the subplatysmal fat pad in place. Deep neck reduction was therefore a necessary component of the operation.
The upper eyelid dermatochalasis was addressed at the same time as a bilateral upper blepharoplasty, on functional grounds — the hooding had begun to encroach on the superior visual field.
A deep plane face and neck lift was performed bilaterally. The composite flap of skin and SMAS was elevated together and the facial retaining ligaments released, allowing the flap to be repositioned as a single unit along a defined vector rather than by skin tension. The jowling, the nasolabial folds and the mandibular border were addressed together as one repositioned unit.
A partial resection of the submandibular glands was performed bilaterally. Both glands were low-lying and full, projecting directly into the submandibular contour. Reduction of gland volume is not addressed by a standard neck lift and formed part of the deep neck work.
The hypertrophic anterior bellies of the digastric muscles were resected. A prominent digastric belly projects into the submental triangle and acts on the cervicomental angle independently of the skin, platysma and glands.
The deep fat pad sitting beneath the platysma was resected under direct vision. This layer sits beyond the reach of subcutaneous liposuction. Together with the gland and digastric work, this completed the deep neck reduction, addressing the glandular, muscular and fat components of the obtuse cervicomental angle.
Fat was harvested, processed and grafted along the mandibular border and face bilaterally, placing structural volume in the regions identified as volume-deficient at preoperative assessment.
Excess upper eyelid skin was excised bilaterally, addressing the hooding that had progressively encroached on the superior visual field.
The photographs below were taken at six weeks postoperatively. At this timepoint the change in the submental and submandibular contour reflects the deep neck component of the operation, which acts on structures that skin and platysma surgery do not reach. What any individual patient can expect depends on their own anatomy, the underlying cause of their neck contour and their healing, and can only be assessed in consultation.
Some swelling remains through the face and neck at six weeks. Swelling after deep neck work takes longer to settle than after skin and SMAS surgery alone, and continues to resolve over the following weeks to months. The contour shown is not the settled result.
Recorded at the six-week review:
Recovery from combined face and neck lift surgery, deep neck reduction and blepharoplasty follows a general pattern, though it varies between individuals:
This is major surgery, performed under general anaesthesia, and it requires a recovery period. All surgery carries risk. The following list is not exhaustive, and the risks relevant to any individual are discussed at consultation:
A GP referral is required before a cosmetic surgery consultation, and a seven-day cooling-off period applies before proceeding with cosmetic surgery. A second opinion is encouraged.

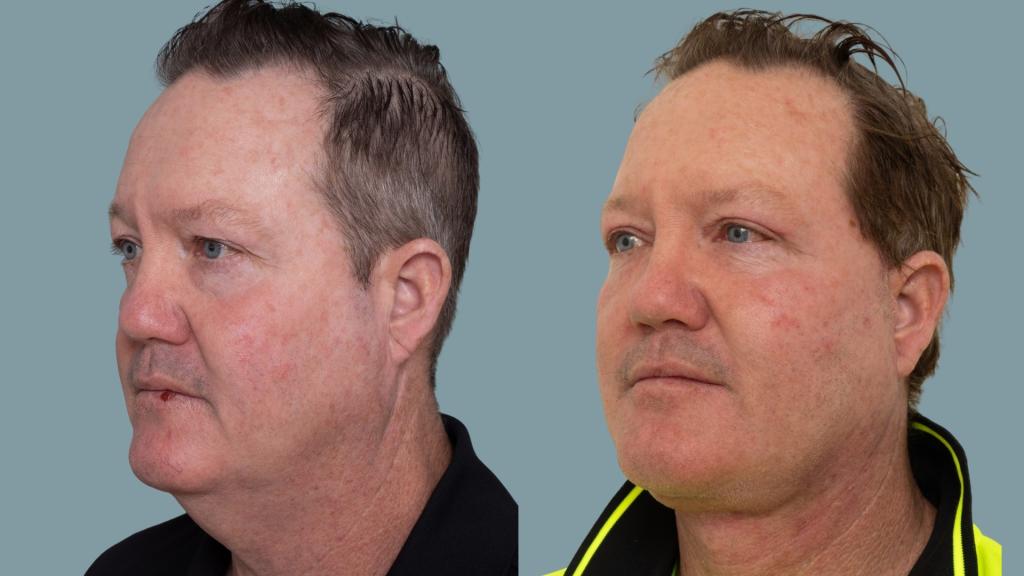
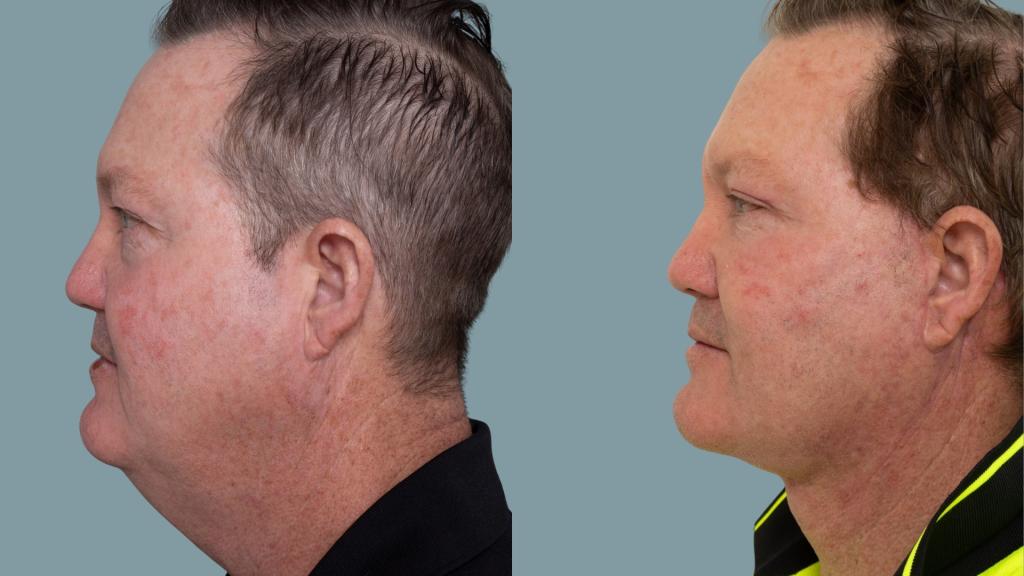
Clinical photography: preoperative and 6 weeks postoperative.
Preoperative (left) & 6 weeks postoperative (right), shown in frontal, oblique and lateral views. The photographic backgrounds have been standardised; no alteration has been made to the patient or to the clinical result.
This result is specific to this patient. It is shown with the patient’s consent and is not a prediction of any other person’s result. Outcomes vary between individuals according to anatomy, healing and other factors. These images are taken at six weeks, when some swelling is still present and the final contour has not yet settled.
| Component | Detail |
|---|---|
| Procedure | Deep plane face and neck lift with deep neck reduction and autologous fat grafting |
| Facelift technique | Deep plane |
| Neck lift technique | Deep plane with deep neck reduction |
| Deep neck reduction | Bilateral submandibular gland resection; bilateral digastric muscle resection; subplatysmal fat resection |
| Blepharoplasty | Bilateral upper blepharoplasty |
| Previous surgery | None |
| Volume restoration | Structural autologous fat grafting — mandibular border and face, bilateral |
| Photography | Preoperative & 6 weeks postoperative |
AHPRA compliance notice: This case study is intended for general information purposes only. Individual outcomes vary, as the result experienced by one person does not necessarily reflect the result another person may experience. All surgical procedures carry risks and require a recovery period — further information is available at Risks of Surgery. Results shown are specific to this patient and cannot be guaranteed for others. Surgery should only be considered after thorough consultation with an appropriately qualified Specialist Plastic Surgeon, and a second opinion is encouraged. This content does not constitute medical advice.
Dr David Sparks — Specialist Plastic Surgeon | FRACS (Plast.) | MED0001863770 | The Coastal Clinic, Southport QLD | Fraser-Kirk Plastic Surgery, Sunshine Coast QLD







All surgery and invasive procedures carry risks. Before proceeding, you should seek a second opinion from an appropriately qualified health practitioner. Read our full information on the risks of surgery. Dr David Sparks — Specialist Plastic Surgeon, MED0001863770.
