Fraser-Kirk Plastic Surgery
Sunshine Coast
Level 3/37 The Esplanade,
Maroochydore QLD 4558
Patient profile
Age: Early 60s | Sex: Female | Previous treatments: Lip and facial filler; neuromodulator injections; IPL | Photography: Preoperative & 6 weeks postoperative
The vertical distance between the base of the nose and the upper lip increases with age. The philtral columns lengthen, the upper lip descends, and the amount of vermilion (the red part of the lip) visible at rest decreases. These changes are gradual and are part of normal facial ageing.
This case describes upper and lower lip surgery in a woman in her early 60s. Assessment identified lengthened philtral columns, an elongated upper lip with reduced vermilion show, and a lower lip smaller than the upper lip at rest. The operative objectives were to shorten the upper lip, increase vermilion show at rest, place volume in both lips, and adjust the proportion between the upper and lower lips.
Clinical evaluation identified the following features:
Filler adds volume. It does not change the vertical length of the upper lip. Where the principal finding is a lengthened upper lip, adding volume increases its projection and weight without altering the distance between the nose and the lip.
Neuromodulator injections can temporarily evert the upper lip, but the effect wears off within months and does not alter lip length. Light-based and laser treatments act on the quality of the skin, not on the structure of the lip. Shortening the upper lip requires surgery. For some patients, particularly where upper lip length is already in proportion, non-surgical options remain appropriate. Suitability for either approach is assessed individually.
The operative plan combined a subnasal lip lift with orbicularis (deep plane) resuspension and micronised fat grafting to both the upper and lower lips. Each element addresses a different finding. The lip lift addresses length: it shortens the upper lip and everts the vermilion. The fat grafting addresses volume and proportion: it places volume in both lips, with more in the lower lip.
The lift was carried on the orbicularis oris muscle beneath the skin rather than on the skin closure itself. Tension on a skin closure is one of the factors associated with scar widening and with the lip stretching back after surgery, so placing the correction on the deeper muscle layer allows the skin to be closed with minimal tension. Technique selection is a matter of individual clinical judgement.
A strip of skin was removed from directly beneath the nose, with the incision placed along the natural curve where the base of the nose meets the upper lip. This shortens the philtral columns and the upper lip as a whole, and everts the vermilion so that more of the red lip sits in view at rest. The incision is positioned within the shadow of the nasal base.
The orbicularis oris (the circular muscle of the lip) was resuspended to the deeper tissues at the base of the nose. The muscle carries the lift, so the skin can be closed with minimal tension.
Fat was harvested, purified by centrifugation, and then micronised by passing it through a mechanical micronisation device at 1200 microns. Micronising the fat produces a finer graft that passes through small cannulas and can be placed precisely within the lip, where irregularity is easily seen and felt.
Targeted placement delivered 3 cc to the upper lip and 4 cc to the lower lip. The larger volume in the lower lip was planned to address the inverted ratio between the upper and lower lips noted at assessment.
Not all transplanted fat survives. A proportion is reabsorbed in the weeks after surgery as the graft establishes a new blood supply, and the lips, which move constantly with speech and expression, are among the more demanding sites for a graft. For this reason the lips were deliberately over-grafted at the time of surgery.
This means the lips appear fuller than intended in the early weeks. As swelling resolves and the graft settles over the following months, volume reduces. Grafting only to the intended final volume on the day of surgery typically leaves the lip under-corrected.
Where significant residual hyaluronic acid filler is present, it may be dissolved before or during surgery so that planning is based on the patient’s own anatomy rather than product layered over it. In this case minimal residual filler remained from a single treatment many years earlier, so dissolving was not required.
The photographs below were taken at six weeks postoperatively. At this timepoint swelling is still present and the lips remain over-grafted, so the volume shown is not the settled result. The fat graft continues to integrate over the coming months, and the scar continues to mature for up to a year. What any individual patient can expect depends on their own anatomy and healing, and can only be assessed in consultation.
Recorded at the six-week review:
Recovery from a lip lift with fat grafting follows a general pattern, though it varies between individuals:
All surgery carries risk and requires a recovery period. The following list is not exhaustive, and the risks relevant to any individual are discussed at consultation:
A GP referral is required before a cosmetic surgery consultation, and a seven-day cooling-off period applies before proceeding with cosmetic surgery. A second opinion is encouraged.
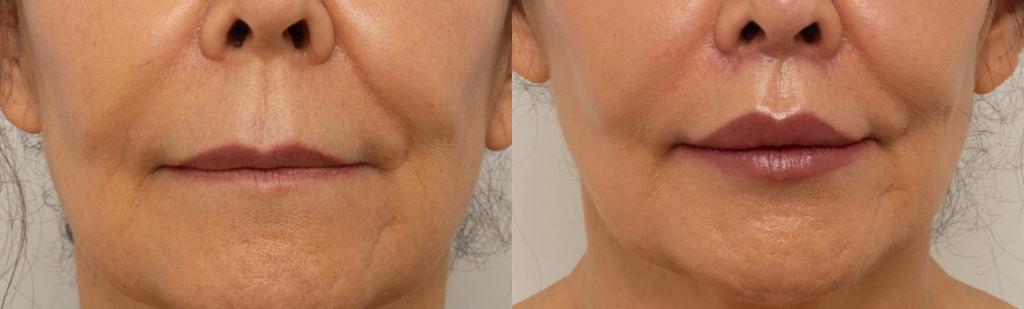
Standardised clinical photography: preoperative and 6 weeks postoperative.
Preoperative (left) & 6 weeks postoperative (right), shown in frontal view. Images are unedited, with no filters, retouching or alteration, and both were taken under standardised conditions with the same lighting, camera angle, framing and positioning.
This result is specific to this patient. It is shown with the patient’s consent and is not a prediction of any other person’s result. Outcomes vary between individuals according to anatomy, healing and other factors. These images are taken at six weeks, when some swelling is still present and the final contour has not yet settled.
The video shows the subnasal scar at six weeks postoperatively. At this stage the scar is still maturing and may appear pink. It sits within the shadow at the base of the nose and continues to fade and soften over the months ahead. Scar healing varies between individuals.
| Component | Detail |
|---|---|
| Procedure | Subnasal lip lift with orbicularis resuspension and micronised autologous fat grafting |
| Lip lift technique | Subnasal, with the incision placed at the base of the nose |
| Muscle management | Orbicularis oris (deep plane) resuspension, minimising tension on the skin closure |
| Fat processing | Harvest and centrifugation, then mechanical micronisation (1200 µm) |
| Volume restoration | Targeted micronised fat grafting: upper lip 3 cc, lower lip 4 cc, with deliberate over-grafting |
| Filler management | Dissolving not required; minimal residual filler from a single remote treatment |
| Previous treatments | Lip filler (once, remote); facial filler (more than 10 years); neuromodulator injections; IPL |
| Photography | Preoperative & 6 weeks postoperative, frontal view |
| Video | Subnasal scar at 6 weeks postoperative |
AHPRA compliance notice: This case study is intended for general information purposes only. Individual outcomes vary, as the result experienced by one person does not necessarily reflect the result another person may experience. All surgical procedures carry risks and require a recovery period. Results shown are specific to this patient and cannot be guaranteed for others. Surgery should only be considered after thorough consultation with an appropriately qualified Specialist Plastic Surgeon, and a second opinion is encouraged. A GP referral is required, and a seven-day cooling-off period applies before cosmetic surgery. This content does not constitute medical advice. For more information, see risks of surgery.
Dr David Sparks — Specialist Plastic Surgeon | FRACS (Plast.) | MED0001863770 | The Coastal Clinic, Southport QLD | Fraser-Kirk Plastic Surgery, Sunshine Coast QLD







All surgery and invasive procedures carry risks. Before proceeding, you should seek a second opinion from an appropriately qualified health practitioner. Read our full information on the risks of surgery. Dr David Sparks — Specialist Plastic Surgeon, MED0001863770.
